About Us
It is a long established fact that a reader will be distracted by the readable content of a page when looking at its layout.

It is a long established fact that a reader will be distracted by the readable content of a page when looking at its layout.
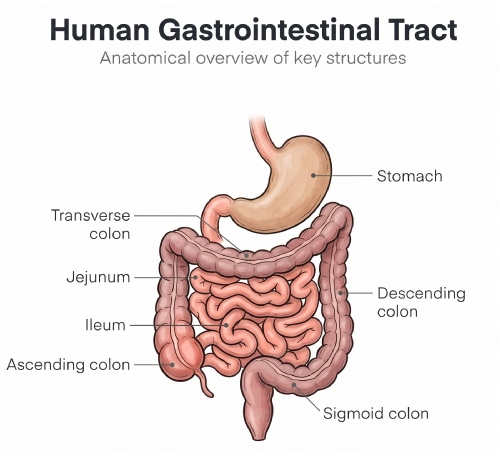
AnaBios recovers human tissue from across the GI tract, based on availability and your study requirements:
• Colon: ascending, transverse, descending and sigmoid
• Small intestine: ileum and jejunum
• Stomach
Region matters for translation. Immune cell populations, epithelial function and disease involvement differ along the gut, so matching the region to your target and indication keeps data relevant to the target patient population. Ulcerative colitis, for example, typically calls for colonic tissue, while Crohn’s disease studies may need ileum.
Our current human colon tissue assay uses biopsies prepared from the mucosa-submucosa layer. These samples retain the epithelium, lamina propria immune cells and submucosal stroma in their native tissue architecture, making them well suited for ex vivo GI models to evaluate inflammation, efficacy, mechanism of action, safety and toxicity.
GI tissue is supplied fresh, so it’s ready for functional ex vivo work rather than limited to fixed or frozen endpoint analyses.
Yes. Through our network of tissue procurement partners, we source IBD tissue, including Crohn’s disease and ulcerative colitis, along with tissue from donors with IBS and other GI indications. We work with predefined disease criteria, so donors match the diseased population of interest.
Testing in diseased GI tissue puts compounds against the inflamed or remodeled tissue state you’re trying to treat, not an induced artificial model of it. Pairing it with healthy tissue from the same region gives you a direct disease-versus-normal comparison.
Availability of specific indications depends on surgical volume, donor recruitment and inclusion criteria. We confirm feasibility during project scoping, before committing to a study timeline.
Each sample comes with donor demographic and clinical information, including age, sex, medical history and medications. For diseased tissue, we also provide disease duration and severity.That data helps stratify responses and account for prior treatment when you interpret efficacy signals. It also supports multi-donor designs that capture the variability you’ll see in clinical populations.
Native human tissue keeps the architecture, multiple relevant cell types and tissue-specific microenvironment that cell lines and many organoid systems lack. Epithelial, immune and stromal cells stay in their native context, so compound effects reflect the cell-to-cell signaling that drives GI disease.
Human tissue also gives a direct read on human-specific responses. That helps address the species differences that can complicate translating results from rodent models of colitis or fibrosis.
Human GI tissue complements these systems rather than replacing them. Organoids and cell lines offer throughput, and rodent models offer whole-organism context. Adding human tissue data gives you translational evidence closer to the clinical setting before you advance a candidate.
Researchers use human GI tissue for efficacy, proof-of-concept, mechanism-of-action, and safety and toxicity studies in inflammatory and fibrotic diseases, including IBD. It’s also a practical tool for investigating mechanisms behind clinical GI signals, such as diarrhea or other GI adverse events seen in trials.
When you’d rather have AnaBios run the work, our GI studies focus primarily on efficacy, with safety endpoints added as needed. They can also be combined with other AnaBios platforms, such cardiac safety, for multi-organ study designs. Learn more about our functional assays.
Tell us your target region, tissue format, disease criteria and donor requirements, and we’ll confirm availability and recommend the best approach for your study. Contact our team to get started.
Which human GI tissue regions and formats does AnaBios offer?
AnaBios supplies fresh human colon tissue from the ascending, transverse, descending and sigmoid colon, plus ileum and jejunum. Stomach tissue is available when supply and study design allow. The current format is the colon biopsy, taken from the mucosa-submucosa layer.
Can AnaBios source diseased GI tissue?
Yes. AnaBios sources IBD tissue, including Crohn’s disease and ulcerative colitis, plus tissue from donors with IBS and other GI indications. Donors can be selected against predefined disease criteria. Availability varies with surgical volume and donor recruitment, so we confirm feasibility during scoping.
What donor information comes with human GI tissue?
Each sample includes donor age, sex, medical history and medications. Diseased tissue also comes with disease duration and severity. Researchers use this data to select donors, stratify responses and account for prior treatment.
How many donors does a typical human GI tissue study use?
An AnaBios-run GI study typically uses four to six independent donors, with six to 10 biopsies or slices per treatment condition per donor. Most studies evaluate two to five compounds alongside unstimulated and stimulated tissue controls. Standard packages and custom designs are both available.
How does human GI tissue compare with organoids and animal models?
Native human GI tissue retains the architecture, multiple cell types and microenvironment that organoids and cell lines often lack, and it avoids the species differences of rodent models. It works best alongside those systems, adding human translational evidence before a candidate advances.
Can human GI tissue help explain a clinical GI signal?
Yes. Human GI tissue can help characterize the mechanisms behind clinical GI findings, such as diarrhea or other GI adverse events seen in trials. Testing a compound directly in human tissue can inform how those findings are interpreted.
Can GI tissue studies be combined with other AnaBios platforms?
Yes. GI studies can be paired with other AnaBios platforms, such as cardiac safety, to evaluate multiple organ systems or safety endpoints in one integrated design.
Can human GI tissue studies be customized?
Yes. AnaBios offers standard study packages and fully custom designs built around your compounds, endpoints, tissue region and disease criteria. Tissue is also available for studies run in your own lab.
